
Cellulitis Skin Infection: Early Signs, Abscess Ultrasound, Sepsis Red Flags & IV Antibiotic Care
Bellaire ER is a freestanding emergency room at 5302 Bellaire Blvd, open 24/7/365. Walk in or call ((713) 660-0001) anytime.
- Open now, 24/7/365
- Walk in, no appointment needed
- 5302 Bellaire Blvd, free parking
Clinical Triage Answer: Cellulitis (ICD-10 L03.90) is an acute bacterial infection of the deep dermis and subcutaneous fat that causes a warm, swollen, tender, expanding area of red skin, most often on the lower leg (ICD-10 L03.115 / L03.116) or arm. Go to a 24/7 emergency room right away if skin redness expands rapidly, is accompanied by fever or chills, involves the face, eye socket, or a joint, causes pain out of proportion to how the skin looks, or occurs in someone with diabetes or immune suppression.
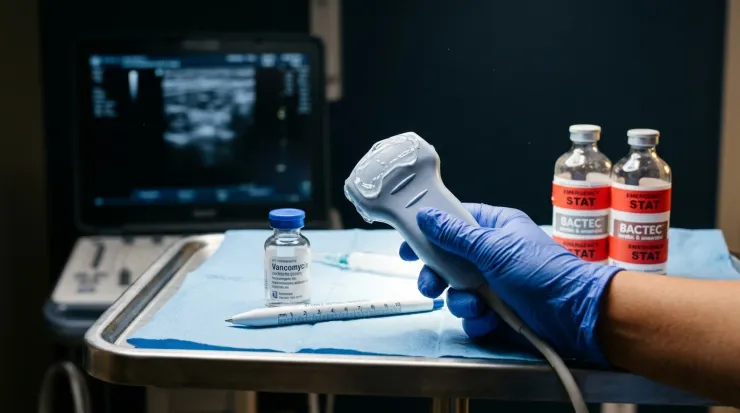
At Bellaire ER (5302 Bellaire Blvd, Bellaire, TX 77401), board-certified emergency physicians evaluate and treat skin infections and abscesses 24/7 using high-frequency soft-tissue ultrasound, on-site sepsis and blood culture labs, bedside abscess drainage when needed, and intravenous antibiotics.
How Bacteria Breach the Skin Barrier
Healthy intact skin keeps surface bacteria out of deeper tissues. Cellulitis starts when bacteria, most commonly beta-hemolytic Streptococcus or Staphylococcus aureus (including methicillin-resistant Staphylococcus aureus, CA-MRSA), enter through a break in the skin that may be too small to notice:
- A minor cut or puncture wound
- An insect bite or animal scratch
- Cracked skin between the toes from athlete’s foot (
tinea pedis) or eczema - A second-degree burn or surgical incision
- Chronic leg swelling (
lymphedemaor venous insufficiency), which stretches skin pores and slows local immune drainage
For tips on protecting broken skin before infection starts, see our companion guide on how to prevent cellulitis and common symptoms of skin infections.
Cellulitis vs. Cutaneous Abscess: Why Bedside Ultrasound Changes Treatment in 56% of Cases
One of the most important decisions in the emergency room is separating non-purulent cellulitis (ICD-10 L03.90) from a cutaneous abscess (ICD-10 L02.91). According to the Infectious Diseases Society of America (IDSA) Practice Guidelines authored by Dr. Dennis Stevens and colleagues (PMID: 24973422), the two conditions are caused by different primary bacteria and require completely different treatments:
- Non-Purulent Cellulitis: Diffuse bacterial spreading through the dermis without a drainable pocket of pus. Cutting into simple cellulitis does not help and damages tissue; treatment is targeted oral or intravenous antibiotics.
- Cutaneous Abscess: A walled-off cavity of pus under the skin, most often caused by community-associated
MRSA. Antibiotics alone cannot penetrate a tense pus cavity. The primary cure is sterile incision and drainage (I&D), paired with MRSA-active antibiotic therapy. In a multicenter randomized trial of 1,247 emergency department patients published in the New England Journal of Medicine by Dr. David Talan and colleagues (PMID: 26962903), adding trimethoprim-sulfamethoxazole after abscess drainage boosted clinical cure rates and cut repeat surgical drainage procedures by more than half (3.4% vs. 8.6%) while reducing new skin infections (3.1% vs. 10.3%).
Because tense swelling makes deep abscesses and simple cellulitis feel identical to a gloved hand, physical exam alone frequently misses hidden fluid pockets. In a prospective emergency department study of 126 adult cellulitis patients published in Academic Emergency Medicine by Dr. Vivek Tayal and colleagues (PMID: 16531602), performing a bedside soft-tissue ultrasound changed physician management in 56% (71/126) of patients, uncovering hidden abscesses that needed drainage in 48% (39/82) of patients initially thought to have simple cellulitis, and preventing unnecessary incisions in patients who had no pus pocket. In the companion ABSCESS Study by Dr. Benjamin Squire and colleagues (PMID: 15995090), emergency bedside ultrasound achieved 98% sensitivity compared with 86% for physical exam alone.
Red Flags: Sepsis, Orbital Cellulitis & Necrotizing Fasciitis
Most localized cellulitis responds well when caught early, but three patterns require immediate emergency room evaluation:
- Systemic Infection & Early Sepsis (
SIRSCriteria,ICD-10 R65.20): Under the IDSA Guidelines (PMID: 24973422), intravenous antibiotics are indicated whenever skin infection is accompanied by fever (> 100.4°F / 38.0°C) or hypothermia (< 96.8°F / 36.0°C), a heart rate above90 bpm, breathing faster than24 breaths/min, red lymphatic streaks (lymphangitis) climbing toward the groin or armpit, low blood pressure, or confusion (sepsis care). - Facial or Periorbital/Orbital Cellulitis: Infection around the eye socket (eye infections) or the center of the face can spread backward into the orbit or intracranial venous sinuses. Pain with eye movement, bulging of the eye, double vision, or eyelid swelling that blocks vision requires immediate IV antibiotics and CT imaging.
- Necrotizing Fasciitis (
ICD-10 M72.6): A surgical emergency that tracks rapidly along deep fascial planes underneath the skin. As detailed by Dr. Chin-Ho Wong and colleagues in Critical Care Medicine (PMID: 15241098) and Dr. Stephanie Bonne and Dr. Sameer Kadri (PMID: 28779832), warning signs include severe pain out of proportion to the surface exam, wooden-hard subcutaneous tissue, purple or bronze skin discoloration, hemorrhagic blisters (bullae), gas crackling under the skin (crepitus), or skin numbness. Emergency physicians use blood biomarkers (CRP, white blood cell count, hemoglobin, sodium, creatinine, and glucose, the LRINEC score, where a score>= 6carries a 92% positive predictive value in validation studies) alongside CT imaging and immediate surgical transfer.
Read when to go to the ER for skin infections and is a skin infection an emergency for a quick checklist.
What Happens During a Skin Infection Visit at Bellaire ER
At Bellaire ER, our board-certified emergency physicians evaluate adult and pediatric skin infections 24/7 at 5302 Bellaire Blvd:
- High-Frequency Soft-Tissue Ultrasound: Distinguishes diffuse cellulitis from a drainable abscess in minutes and checks for deep vein blood clots (thrombophlebitis or
DVT), which frequently mimic lower-leg cellulitis. - On-Site Blood & Wound Lab Work: When systemic symptoms or high-risk conditions are present, our on-site laboratory runs a Complete Blood Count (
CBC), Comprehensive Metabolic Panel (sodium,creatinine,glucose), serum lactate, C-reactive protein (CRP), and blood or wound cultures. - Sterile Bedside Abscess Drainage & First-Dose IV Antibiotics: If an abscess is present, the physician numbs the area and performs sterile drainage on site. When IV antibiotics (
cefazolinorvancomycin) are indicated, the first dose starts in the ER before you go home with oral prescriptions and marked skin borders, or before direct hospital transfer if inpatient IV therapy or surgical care is needed.
Walk In 24/7 for Skin Infection & Abscess Care in Bellaire
Do not wait overnight while a painful red rash or swelling expands. Bellaire ER is a licensed freestanding emergency room open 24/7 at 5302 Bellaire Blvd, Bellaire, TX 77401. No appointment is needed; review our insurance information when convenient.
- Get Directions to 5302 Bellaire Blvd
- Call Bellaire ER 24/7: (713) 660-0001
- Optionally Save Your Spot Online (For mild, non-spreading rashes without fever or pain, you can also book a telemedicine visit.)
Frequently asked questions
When should I go to the emergency room for cellulitis?
Go to a 24/7 emergency room right away if skin redness is spreading noticeably over a few hours, if you develop a fever or chills, if the redness is on your face or around your eye, if you see red streaks moving up your arm or leg, or if you have diabetes or a weakened immune system.
How does an emergency doctor tell the difference between cellulitis and an abscess?
Simple cellulitis is a diffuse bacterial infection of the deep skin layers that responds to antibiotics without cutting the skin, whereas an abscess is a walled-off pocket of pus that must be drained. Because deep swelling makes the two look identical from the outside, emergency physicians use high-frequency bedside ultrasound, which detects hidden pus pockets with 98% sensitivity and changes treatment in 56% of patients.
What are the warning signs of necrotizing fasciitis?
Necrotizing fasciitis is a rare, life-threatening deep tissue infection. Warning signs include severe pain that feels far worse than the visible skin redness looks, dusky purple or gray skin patches, fluid-filled blisters, crackling under the skin, numb skin over the swollen area, and high fever.
Why do doctors draw a pen line around cellulitis?
Marking the outer border of redness with a surgical pen lets you and your physician see objectively whether the bacterial inflammation is receding after antibiotics start or continuing to expand across the skin.
Clinical references & peer-reviewed sources
- Practice guidelines for the diagnosis and management of skin and soft tissue infections: 2014 update by the Infectious Diseases Society of America (Clin Infect Dis 2014; Stevens DL et al.)
- The effect of soft-tissue ultrasound on the management of cellulitis in the emergency department (Acad Emerg Med 2006; Tayal VS et al.)
- ABSCESS: applied bedside sonography for convenient evaluation of superficial soft tissue infections (Acad Emerg Med 2005; Squire BT et al.)
- The LRINEC (Laboratory Risk Indicator for Necrotizing Fasciitis) score: a tool for distinguishing necrotizing fasciitis from other soft tissue infections (Crit Care Med 2004; Wong CH et al.)
- Trimethoprim-Sulfamethoxazole versus Placebo for Uncomplicated Skin Abscess (N Engl J Med 2016; Talan DA et al.)
Have Questions About Visiting Bellaire ER?
Call our team at (713) 660-0001 any time with questions about visiting our independent, physician-owned freestanding emergency room at 5302 Bellaire Blvd, open 24/7 with short waits.